

You may have a real choice of halfway house, or the final address may be controlled by a court, corrections agency, probation office, parole authority, or federal reentry system. A person arranging sober living after addiction treatment will usually have far more control than someone entering housing as part of a release plan.
The phrase halfway house also covers several forms of housing in everyday conversation. People use it for federal Residential Reentry Centers, state reentry housing, sober living homes, recovery residences, and some residential treatment programs. Those facilities do not follow one national admission process or one set of housing rules.
Start with the authority behind the placement. If you are paying privately, you may contact homes directly and decide where to apply. If a court or supervising agency controls your housing, an operator saying that a bed is available does not mean you are legally allowed to live there.
Who Actually Decides Where You Can Go?

Private recovery housing gives the resident the most control. You can compare residences, read the rules, ask about fees, visit the property, and decide which homes are worth applying to. The operator still decides if you meet its admission requirements and if a bed is available.
Community supervision changes the process. A probation or parole order may require an approved address, restrict the geographic area, or give a supervising officer authority to reject a proposed residence. Paying a deposit before receiving approval can leave someone committed to housing they are not permitted to use.
| Situation | Who Makes the Decision | What You Can Control |
|---|---|---|
| Federal prison release | Federal Bureau of Prisons and the receiving RRC contractor | You can raise location, employment, treatment, and family concerns, but you cannot reserve any RRC you choose. |
| State parole or probation | The court, supervising agency, or officer under state rules | You may propose an address or receive a list of approved housing. |
| Leaving addiction treatment voluntarily | You and the recovery residence | You can compare available homes and apply directly. |
| Private sober living | You and the operator | Your options are narrowed by admission rules, price, location, and bed availability. |
Anyone under community supervision should read the actual release conditions before paying a deposit. The legal structure behind probation and parole is not identical, and state procedures can change who has authority to approve the address.
Federal Prisoners Do Not Simply Pick an RRC
Jessica Kent describes her own move from prison into halfway-house living in the video below. Her account is useful here because she talks about required meetings, employment, parole obligations, housing costs, and the pressure of rebuilding daily life after release.
Video by Jessica Kent, “WHAT LIFE WAS LIKE IN A HALFWAY HOUSE.” Kent describes her own post-incarceration stay, including required programs, work, parole responsibilities, and the cost of the residence. The video is a third-party personal account and not first-person reporting by this article.
The Federal Bureau of Prisons uses the term Residential Reentry Center, or RRC, for facilities commonly called federal halfway houses. An RRC forms part of the federal correctional reentry system. A prisoner cannot simply reserve a room in one.
The BOP RRC guidance states that an institutional unit team generally prepares an RRC referral recommendation about 17 to 19 months before release. The team includes the unit manager, case manager, and counselor.
Federal law sets the outside limit for pre-release community confinement. 18 U.S.C. § 3624(c)(1) permits the BOP to place an eligible prisoner in pre-release custody during the final portion of the sentence, with community confinement limited to 12 months.
The legal ceiling is not a promise of a 12-month placement. The BOP sets the recommended period for each person after reviewing the individual case.
The Five Factors the BOP Has to Consider
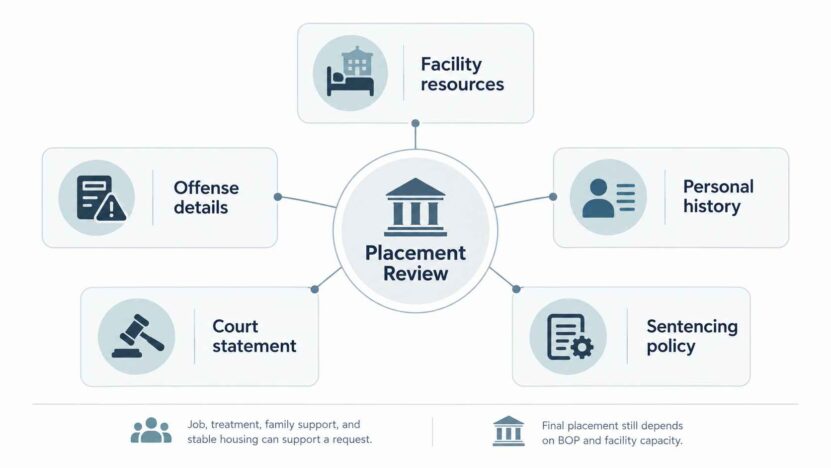
The placement review uses the five factors in 18 U.S.C. § 3621(b).
- The resources of the facility contemplated.
- The nature and circumstances of the offense.
- The history and characteristics of the prisoner.
- Any statement by the sentencing court.
- Any pertinent Sentencing Commission policy statement.
The first factor has a very practical effect. A proposed RRC needs space, the correct contract coverage, and the ability to accept the referral. Someone can have a job, family support, treatment, and a release address ready in one city and still face another placement if the contracted facility serving that area cannot take the referral.
Employment records, scheduled treatment, continuing medical care, family responsibilities, transportation, and a stable release address give the unit team concrete information to evaluate. Those facts support a location request. They do not create a legal right to one particular RRC.
A sentencing judge can recommend a facility or type of placement. Section 3621(b) requires the BOP to consider relevant statements from the sentencing court, but the Bureau makes the final placement decision.
Bed Availability Can Change the Plan
The institutional recommendation is not the final step. The referral moves through the federal reentry system, and the receiving contractor needs enough capacity to accept it.
A request therefore works better when it is tied to facts rather than a general preference for a city. A documented job offer, scheduled treatment, established medical care, or stable family address gives the case manager a concrete reason for requesting that area.
An RRC Still Comes With Correctional Rules

Moving from prison into an RRC gives a resident more access to the community, but the person remains in a structured correctional setting. Employment schedules, approved absences, sign-out procedures, curfews, testing, and travel can all be controlled by the facility and release plan.
RRC placement is intended to reconnect a resident with employment, financial responsibilities, family contact, treatment, housing, transportation, and other parts of community life before full release.
The useful questions are specific. How are work hours approved? What happens if an evening shift runs past curfew? How are medical appointments recorded? Which trips need permission? What happens when a bus delay makes someone late returning to the facility?
Answers to those questions tell a resident far more about daily life than a list of amenities.
Recovery Residences Follow Another Structure
A recovery residence provides alcohol-free and illicit-drug-free housing for people living in recovery. Some homes are run mainly by residents. Others have house managers, paid staff, structured programming, case support, or clinical treatment.
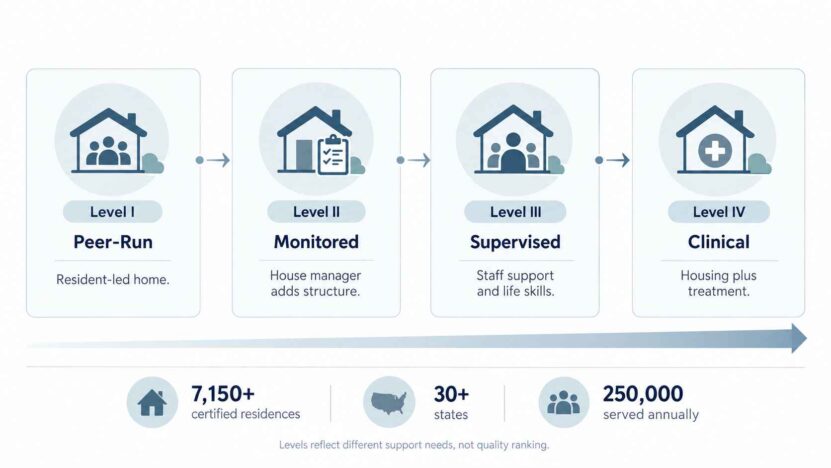
The NARR Standard organizes recovery residences into four levels of support. The framework describes how much structure, staffing, and clinical involvement a residence provides.
| NARR Level | Type | What It Means in Practice |
|---|---|---|
| Level I | Peer-Run | Residents govern the home democratically. Paid onsite staffing is generally absent. |
| Level II | Monitored | A house manager or senior resident adds structure, rules, screening, and peer accountability. |
| Level III | Supervised | Trained or credentialed staff provide structured recovery support and life-skills programming. |
| Level IV | Clinical | Professional staff combine recovery housing with clinical addiction treatment. |
NARR reports more than 7,150 certified residences across more than 30 states, serving about 250,000 people annually. Those figures appear on the NARR organization page.
The level is not a quality ranking. Level I and Level III serve residents who need separate amounts and forms of support. Someone leaving intensive treatment may need regular staff contact and scheduled programming. Another person may be ready for peer-run housing with fewer formal services.
SAMHSA addresses the same placement issue in its recovery housing guidance. The level of housing support should fit the needs, goals, preferences, and recovery plan of the resident.
NARR Certification Runs Through State Affiliates
NARR does not directly certify individual homes. Recognized state affiliates handle certification under the national standard.
The NARR affiliate directory lists those state organizations. A home claiming NARR-based certification should be able to give you the name of the affiliate that issued the credential and the legal name used in the certification record.
The legal name is important because the name on a website or building may be a brand rather than the company shown in certification or licensing records.
Certification and treatment licensing serve separate purposes. A residence providing housing and peer support may operate under a certification framework, yet a connected clinical program may need a behavioral health license from the state.
Treatment Accreditation Belongs to the Entity That Earned It
A sober home and an outpatient treatment center can share a name, owner, website, or referral system without sharing the same accreditation.
The Joint Commission program accredits behavioral health and human services organizations, including addiction treatment providers. CARF has a separate behavioral health accreditation program covering several forms of treatment and support.
An accreditation badge should lead to a specific legal entity, service, and location. Accreditation held by an outpatient treatment center does not automatically extend to a separately operated sober living property.
Get the accredited company name and the address covered by the credential. Then check the accreditor record rather than relying on the logo.
A Treatment Referral Does Not Certify the House
A counselor, treatment center, or case manager may give someone several housing names during discharge planning. A referral tells you who suggested the home. It does not prove that the residence holds every certification or license mentioned in its advertising.
FindTreatment.gov is the federal SAMHSA locator for mental health and substance use treatment providers. It is not a national certification registry for sober living homes.
For housing, the relevant source may be a state recovery residence certifier, behavioral health agency, or another state registry. For clinical treatment, the state licensing agency and any claimed accreditor are more useful.
Searching becomes much easier once you have the full legal name of the operator. A brand name may not reveal the company that signed the lease, collected the rent, or held the license.
Patient Brokering Has Led to Federal Convictions

Recovery housing can sit beside treatment, transportation, drug testing, and insurance billing. Problems begin when someone earns undisclosed money or another benefit because a resident was sent to a particular provider or laboratory.
United States v. Michael J. Ligotti, Case No. 9:20-CR-80092-RAR in the U.S. District Court for the Southern District of Florida, provides one documented example. Ligotti pleaded guilty in October 2022 to conspiracy to commit health care and wire fraud under 18 U.S.C. § 1349.
The DOJ case record states that Ligotti worked as an authorizing physician for addiction treatment facilities and sober homes in South Florida. Prosecutors accused him of authorizing unnecessary testing and treatment used to generate insurance claims. He was initially sentenced to 240 months in prison in January 2023 and ordered to pay $127,427,987.74 in restitution. The court reduced his prison term to 120 months in December 2023 after substantial cooperation with law enforcement.
United States v. Kenneth Chatman, Case No. 17-80013-DMM in the same federal district, involved sober homes and addiction treatment centers in Palm Beach and Broward counties. Chatman pleaded guilty to conspiracy to commit health care fraud under 18 U.S.C. § 1349, money laundering conspiracy under 18 U.S.C. § 1956(h), and sex trafficking conspiracy under 18 U.S.C. § 1594(c).
The 2017 federal sentencing record states that U.S. District Judge Donald M. Middlebrooks sentenced Chatman to 330 months in prison. Prosecutors said insured residents received free or reduced rent and other benefits, then were directed into treatment and repeated drug testing that generated insurance claims.
Ask Who Orders the Test and Who Gets Paid
We would not accept “the house handles it” as a useful answer when mandatory testing can generate a separate medical bill. Get the names and payment chain in writing.
- Who orders the test? Get the name of the clinician or provider responsible for the order.
- Which laboratory performs it? Get the legal company name, not only the collection-site name.
- Who receives the bill? Find out if the charge goes to insurance, the resident, the treatment provider, or another payer.
- Who earns money from the referral? Ask if the residence, owner, treatment center, or another connected company receives payment or another benefit.
If staff refuse to identify the laboratory or explain who receives payment, stop until the financial arrangement is clear.
The Federal Anti-Kickback Statute Covers More Than Cash
The federal Anti-Kickback Statute prohibits knowingly offering, paying, soliciting, or receiving something of value to induce or reward referrals involving services paid by federal health care programs.
The HHS fraud guidance explains that illegal remuneration is not limited to cash. Free rent, hotel stays, meals, or excessive consulting payments can create legal problems when tied to federally reimbursed referrals.
Free housing is therefore not automatically a no-strings benefit. A resident offered free rent, transportation, or a scholarship only if they attend one named treatment provider should find out who pays for the benefit and what the housing company receives in return.
Legitimate financial assistance exists. Refusal to explain the arrangement is the warning.

Florida Law Contains Specific Referral Exceptions
Florida gives one of the clearest statutory examples of how treatment referrals and recovery residences can be regulated.
Florida Statute 397.4873 generally prevents a licensed substance abuse provider from sending a patient to, or accepting one from, a recovery residence unless the residence has a valid certificate of compliance and is actively managed by a certified recovery residence administrator.
Subsection 397.4873(2) lists exceptions. They include referrals involving certain providers operating under contract with a managing entity, qualifying referrals where the recovery residence receives no direct or indirect benefit, a narrow provision involving certain wholly owned subsidiaries tied to referrals made before July 1, 2018, and qualifying resident-run homes with no prohibited financial or referral relationship.
Subsection (3) imposes another restriction despite those exceptions. A licensed provider cannot make or accept a referral involving a residence that permits alcohol, illegal drugs, marijuana as defined by the statute, or use of prescription medication by someone other than the person for whom it was prescribed.
Florida also has a separate patient brokering statute covering commissions, bonuses, kickbacks, rebates, bribes, and other benefits connected to patient referrals.
Florida Certification Records Give You a Document Checklist
Florida Statute 397.487 requires a recovery residence seeking certification to provide operating documents that are directly useful to someone deciding if the home is safe to enter.
| Document | Why You Need It | Comparable Rule in Another State |
|---|---|---|
| Resident rules | They show curfews, visitor limits, conduct rules, medication policies, and testing requirements. | Minnesota § 254B.216 requires certified residences to document that residents received residence rules from January 1, 2027. |
| Intake procedures | They show what screening, documents, agreements, and information are required before admission. | Kentucky 908 KAR 1:410 sets certification and resident-policy requirements. |
| Relapse policy | You need to know what follows a return to use or positive test before a crisis occurs. | Minnesota § 254B.216 requires residents to receive the relapse policy from January 1, 2027. |
| Fee schedule | It shows which charges belong to housing and which costs may sit outside the advertised rent. | Kentucky 908 KAR 1:410 requires written financial obligations, fees, charges, rents, and collection terms. |
| Refund policy | It tells you what happens to prepaid money after an early move or discharge. | Minnesota requires disclosure of the refund policy. Kentucky also regulates refund and deposit terms. |
| Eviction procedures | They explain how removal works and what process the residence follows. | Minnesota resident protections require written orientation and residence policies from January 1, 2027. |
| Code of ethics | It gives residents a written standard for operator and staff conduct. | Kentucky requires a Recovery Housing Code of Ethics as part of certification. |
| Insurance documentation | It confirms that the operator carries coverage required under the certification system. | Kentucky requires proof of commercial general liability insurance. |
| Background screening | Florida requires screening connected to specified owners, directors, and financial officers. | Kentucky certification rules include staff and compliance requirements tied to resident safety. |
| Fire, safety, and health records | They show that the property met inspections required by the certification process. | Kentucky requires compliance with applicable zoning, ordinances, and building codes. |
Florida also requires an onsite inspection after a complete certification application is received. Ask for the relevant policies and fee documents before paying a deposit, not after a dispute starts.
Ask Who Owns the Housing, Treatment, and Laboratory Companies
Three companies with separate names can still share owners, managers, investors, marketing operations, or referral agreements.
Get the legal name of the company collecting rent. Then get the legal name of any treatment provider residents are expected to attend. If testing is mandatory, get the laboratory name too.
If staff say treatment is optional, compare that claim with the written housing agreement. A house requiring every resident to attend one named outpatient provider has created a direct connection between housing and treatment, even if two companies send separate bills.
Shared ownership is not automatically unlawful. Hidden financial incentives are the concern. A resident should know which company receives payment for each service and which services are conditions of keeping the bed.
Insurance Approval for Treatment Does Not Automatically Pay the Rent
View this post on Instagram
Clinical treatment and housing are separate expenses in many recovery arrangements. An insurer may cover therapy, medication management, psychiatric services, or another covered health service and still leave the resident responsible for housing.
A CMS housing report explains that federal Medicaid funding is generally unavailable for room and board outside certain medical institutions. Medicaid can still cover eligible health and support services delivered to someone living in community housing.
The Medicaid institutional rules describe settings where room and board form part of a covered institutional benefit. A sober living home does not become one of those settings simply because residents receive Medicaid-funded treatment elsewhere.
The useful question is not only, “Do you take insurance?” Get the housing charge, the treatment charge, the amount expected from insurance, and the balance that remains with the resident.
Recovery Housing Has No Reliable National Rent Price
There is no single monthly figure that accurately describes recovery housing across the United States. Local housing prices, staffing, services, subsidies, residence structure, and program requirements all affect the amount charged.
Amy A. Mericle, Jennifer Miles, and John Cacciola examined a stratified random sample of 25 Philadelphia recovery homes in the Journal of Psychoactive Drugs in 2015. Their study, A Critical Component of the Continuum of Care, reported a mean monthly resident fee of $340.40, with a standard error of $18.60.
The Philadelphia figure describes the monthly resident fee reported by that sample at that time. The published abstract does not separate the $340.40 into rent, utilities, food, testing, or individual program charges. It should not be presented as a current rent-only figure or a national price.
Amy A. Mericle, Katherine J. Karriker-Jaffe, Shalika Gupta, David M. Sheridan, and Doug L. Polcin published another study in 2016 covering 260 sober living houses in Los Angeles County.
The Los Angeles study split homes into those charging less than $1,400 per month and those charging $1,400 or more. Researchers used the cutoff to examine the geographic distribution of lower-cost and higher-cost houses and neighborhood characteristics associated with those locations.
The $1,400 figure was an analytical threshold for that study. It was not a national rent recommendation and did not test which price produced stronger recovery outcomes.
A 2026 National Study Looked at Operating Costs

Madison Ashworth, Grace L. Clancy, David Johnson, Robin A. Thompson, and colleagues published The Business of Recovery in the Substance Use & Addiction Journal in 2026.
The researchers used a cross-sectional survey of 408 recovery housing organizations operating 1,458 residences in 19 states. Data collection ran from January 2024 through February 2025.
Among 265 organizations that reported estimated annual operating costs, the median 2023 operating cost was $155,000 per organization. The median annual operating cost per resident served was $6,464.
Those numbers describe provider operating costs, not the rent paid by one resident. Resident fees were the largest revenue source on average, yet many organizations reported that they did not collect every fee charged.
A Fee Schedule Should Separate Every Charge
Rent is only the starting number. Deposits, transportation, testing, food, utilities, admission charges, and treatment can turn a cheaper-looking residence into the more expensive option.
| Charge | What to Confirm | How It Can Change the Total |
|---|---|---|
| Rent | Weekly or monthly rate and due date | The advertised figure may cover housing only. |
| Deposit | Refundable or nonrefundable | Early discharge can affect how much money comes back. |
| Transportation | Included rides, mileage, or per-trip fee | Daily trips to work or treatment can add hundreds of dollars. |
| Drug testing | Who orders it and who bills for it | Laboratory billing can sit outside the housing charge. |
| Food and utilities | Included or resident responsibility | Several recurring charges can erase the apparent saving in rent. |
| Treatment | Provider, insurance billing, and resident balance | Clinical services can generate a separate bill. |
| Administrative fees | Amount and refund terms | Some are due before move-in and may not be returned after early departure. |
A simple calculation shows why transportation needs its own line. Suppose Residence A costs $200 less each month but requires two $15 rides every workday. Twenty workdays would create $600 in rides, making the supposedly cheaper residence $400 more expensive before weekend travel is counted.
The example is only a calculation. The numbers that belong in the final budget are the prices quoted by the residence, transport provider, and treatment program.
SAMHSA addresses provider financing in its March 2026 report Recovery Housing Funding Sources. Resident fees, public funding, grants, and other revenue streams can all support recovery housing operations.
Read the Discharge Policy Before You Need It
Curfews and chores are easy to discuss during admission. The policy with higher stakes is what happens after a positive test, return to substance use, serious rule breach, or medication issue.
Florida certification law requires a relapse policy, refund policy, and eviction procedures. NARR standards also require written resident agreements and ethical operating practices.
The answer should be specific. Does a positive test mean immediate removal? Is there an assessment first? Can the resident move to another level of care? Who is contacted? How long does the resident have to collect belongings? What happens to rent already paid?
A vague answer such as “we handle it case by case” gives the resident no clear idea what will happen during the moment when housing is most fragile.

Medication Rules Need the Same Specificity
A recovery residence may use locked medication storage, staff-controlled access, resident self-management, or another system. The policy should be clear before move-in.
Anyone receiving buprenorphine, methadone, naltrexone, psychiatric medication, or another ongoing prescription needs the exact rules. Ask how medication is stored, how dosing works, how controlled substances are handled, and how transportation to an outside opioid treatment provider is arranged.
A statement that the home is “medication friendly” does not answer those questions.
Location Has to Work on an Ordinary Tuesday
A quiet neighborhood and clean bedrooms tell you little about the weekly logistics.
Put the address on a map with work, outpatient treatment, probation or parole meetings, pharmacies, medical care, grocery stores, and public transportation. Then calculate the time and cost of getting to each place.
A house that adds two hours of transportation every weekday can interfere with employment and treatment attendance. Another home with a higher rent may cost less overall if work and treatment are within walking distance or on one bus route.
People under supervision also need confirmation that the address complies with court or agency restrictions. The housing operator cannot make that decision for the supervising authority.
Visit the Residence Before Paying

Photographs will not tell you how many residents sleep in each room, who is onsite overnight, how conflicts are handled, or if written rules match daily practice.
An in-person visit gives you the chance to compare the description with the property and collect documents before money changes hands.
- Get the legal operator name. Use it for certification and licensing searches.
- Confirm current certification. Check the issuing organization yourself.
- Get the complete fee schedule. Housing, deposits, transport, testing, and treatment should be separated.
- Read the discharge policy. Get the response to a positive test or serious rule violation in writing.
- Identify the laboratory. Find out who orders tests and who receives the bill.
- Identify treatment affiliations. Get the legal names of programs residents are expected to attend.
- Count the beds. Compare actual bedroom occupancy with what was described before the visit.
- Ask who is onsite overnight. Staffing changes the amount of supervision residents receive.
- Find the complaint process. Residents need somewhere to report problems involving the house manager or operator.
If the operator will not provide basic documents before collecting money, that refusal gives you information you did not have before the visit.
Questions to Ask if You Are on Probation or Parole
A later move can require approval, so housing under supervision comes with another set of questions.
- Is this exact address approved for my supervision?
- Which alternative addresses are already approved?
- Who authorizes a later transfer?
- What happens if the residence removes me?
- How quickly must I report an address change?
- Does the residence report violations directly?
- Are there geographic restrictions on my housing?
- Can employment support a request for another location?
Get those answers from the supervising authority. A residence saying that it accepts residents on parole does not prove that your parole office has approved that address for you.
Longer Sober Living Stays Were Linked With Better 12-Month Outcomes
Meenakshi S. Subbaraman, Elizabeth Mahoney, Amy Mericle, and Douglas Polcin studied length of stay among sober living house residents in California. Their 2023 article appeared in The American Journal of Drug and Alcohol Abuse.
The Subbaraman study analyzed baseline and 12-month data from 455 residents. Researchers classified 284 people who stayed for less than six months as early discontinuers and 171 who stayed for at least six months as stable residents.
At the 12-month follow-up, stable residents recorded 7.76 percentage points more abstinent days than early discontinuers after statistical adjustment. The stable group also had fewer psychiatric symptoms, fewer depression symptoms, lower odds of an ongoing substance use disorder, and lower odds of reported legal problems.
The finding shows an association. It does not prove that six months by itself caused the stronger outcomes. The study still gives residents and operators a concrete reason to take housing stability, affordability, location, and discharge rules seriously.
Red Flags That Need an Explanation Before You Sign
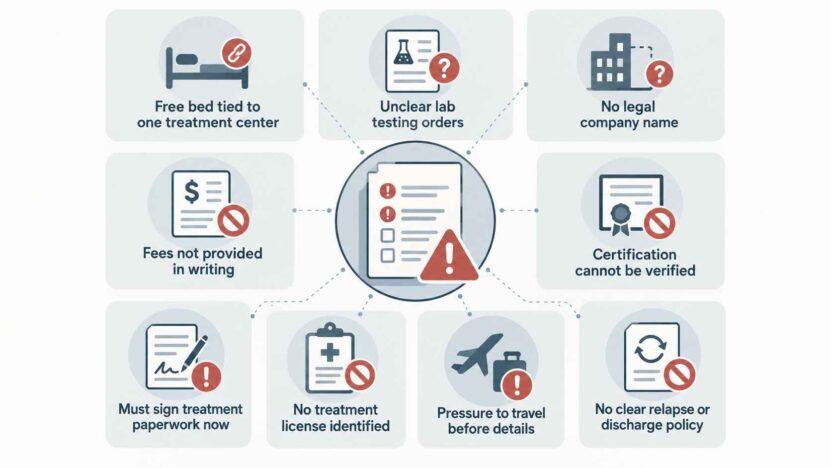
No single uncomfortable answer proves fraud. A group of unexplained financial or operational relationships is enough to stop the process and ask for documentation.
- A free or heavily discounted bed is available only if you attend one named treatment center.
- The residence requires one laboratory but cannot explain who orders the tests.
- Staff refuse to give the legal name of the company collecting rent.
- The operator will not provide fees in writing.
- The website claims certification that cannot be confirmed in the relevant registry.
- Housing depends on signing treatment paperwork immediately.
- The residence advertises clinical care but cannot identify its treatment license.
- A referral company pressures you to travel before naming the residence.
- Staff cannot explain what happens after a positive test or return to use.
The clearest warning is a financial arrangement that nobody will explain. Housing, treatment, transportation, testing, and medication services can all belong in legitimate recovery care. You should still be able to identify who provides each service, who sends the referral, and who gets paid.
The Bottom Line
If you are arranging recovery housing privately, you will usually have substantial control over where you apply. Admission rules, available beds, price, location, certification, and the amount of support will narrow the list.
Federal release, probation, parole, and court-ordered placements work another way. The supervising authority may assign the residence, limit the available providers, or require approval before you move.
Do not rely on one word such as “approved,” “certified,” “covered,” or “recommended.” Confirm who operates the house, who certified or licensed it, what housing costs, which treatment provider is involved, who handles testing, and what happens if the placement ends early.
Get the discharge policy in writing before the deposit clears. If a positive test can lead to immediate removal, the policy should say so. If the operator refuses to put the rule on paper, a verbal promise will not give you much protection later.